Running Head: Adjunctive Psychological Interventions in COPD
Funding Support: This project is supported by the Hong Kong Polytechnic University funding (P0040602 - ZVYT) and (P0052607- ZZUA).
Date of Acceptance: August 6, 2026 | Published Online Date: August 13, 2026
Abbreviations: 6MWD=6-minute walk distance; ATS=American Thoracic Society; BAI=Beck Anxiety Inventory; BDI=Beck Depression Inventory; CAL=chronic airflow limitation; CAT=COPD Assessment Test; CBT=cognitive behavioral therapy; CG1=control group with psychotherapy and physical therapy; CG2=group with physical exercise and physical therapy; CI=confidence interval; COAD=chronic obstructive airway disease; COBD=chronic obstructive bronchopulmonary disease; COPD=chronic obstructive pulmonary disease; DASS=Depression Anxiety Stress Scale; ERS=European Respiratory Society; FEV1 %pred=forced expiratory volume in 1 second percentage predicted; GOLD=Global initiative for chronic Obstructive Lung Disease; GRADE=Grading of Recommendations, Assessment, Development, and Evaluations; HADs=Hospital Anxiety and Depression scale; HADS-A=HADS-anxiety subscale; HADS-D=HADS-depression subscale; HR=hazard ratio; HRQoL=health-related quality of life; MCBT=mindfulness-based cognitive therapy; MCID=minimal clinically important difference; MD=mean difference; MID=minimal important difference; nRCT=nonrandom control trial; PE=physical exercise; PEDro=Physiotherapy Evidence Database; PI=prediction interval; PR=pulmonary rehabilitation; PR+PSY-INT=pulmonary rehabilitation and psychological intervention; PRISMA=Preferred Reporting Items for Systematic reviews and Meta-analyses; PROSPERO=International Prospective Register of Systematic Reviews; PRP=pulmonary rehabilitation program; PSY-INT=psychological intervention; PT=physical therapy; QoL=quality of life; RCT=random control trial; RoB=risk of bias; RP=rehabilitation program; SC=social group; SD=standard deviation; SMD=standardized mean difference
Citation: Cheung CC, Ng GL, Li TS, et al. The combined efficacy of adjunctive psychological interventions and pulmonary rehabilitation in people with chronic obstructive pulmonary disease - a systematic review and meta-analysis. Chronic Obstr Pulm Dis. 2026; 13(5): 416-432. doi: http://doi.org/10.15326/jcopdf.2026.0768
Introduction
Epidemiology and Psychological Burden of COPD
Chronic obstructive pulmonary disease (COPD) is characterized by airflow limitation and breathlessness, which encompasses emphysema and bronchitis/bronchiolitis.1 There are more than half a billion cases worldwide, making COPD the third leading cause of global mortality.2 Aside from physical symptoms such as dyspnea, people with COPD also report anxiety and depression symptoms, or in more severe cases, suffer from psychological disorders.3 According to a 2023 systematic review,4 the overall pooled global prevalence of variably defined depression among people with COPD was 34.5% (95% confidence interval [CI]: 30.9–38.1), with rates in individual studies varying from 17.0% to 61.7%. A higher prevalence was found among hospitalized individuals (40.4% versus 36.5% in out-patient clinics), females (39.7% versus 28.8% in males), and patients with Global initiative for chronic Obstructive Lung Disease (GOLD) stage 3–4 COPD (35.0% versus 28.3% in patients with GOLD stage 1–2).4 Anxiety disorders are also common among inpatient populations (10%–55% versus 13%–46% in outpatients).5
Mechanisms Underlying Anxiety and Depression in COPD
The mechanism leading to the symptoms of anxiety and depression in people with COPD is believed to be multifactorial and bidirectional, forming a pathological cycle that progressively undermines health status.6-8 Specifically, this bidirectional relationship manifests as a vicious cycle between physical and psychological symptoms. Psychological symptoms in people with COPD result from multiple interacting biological, behavioral, and social factors.7-9 Symptoms such as dyspnea, fatigue, cough, and sputum production may induce psychological symptoms.2 When triggered, negative emotions are associated with physical symptoms, leading to maladaptive behaviors and undermining the individual's perception of their own health status.10 For instance, dyspnea is frequently interpreted as threatening.10 Fear could prompt people with COPD to avoid physical activities, leading to a vicious cycle of dyspnea, inactivity, and deconditioning.10,11 Perpetuation of this vicious cycle exacerbates the psychological symptoms of people with COPD, reducing treatment adherence,12 and lowering self-efficacy.13,14 These could in turn diminish physical capacity and worsen disease prognosis, increasing the likelihood of hospitalization and mortality in people with COPD.15
Pulmonary Rehabilitation and Psychological Interventions for People With COPD
Pulmonary rehabilitation (PR) is one of the most common nonpharmacological management strategies for people with COPD, which aims to improve the physical and psychological well-being of individuals with chronic respiratory diseases and encourage long-term adherence to health-enhancing behaviors.16,17 Based on detailed assessments, patient-tailored therapies, including exercises, education, and behavior modification, are prescribed. According to a systematic review summarizing international pulmonary rehabilitation guidance, the supervised exercise-training component is typically recommended for at least 4 weeks, and extending programs beyond 12 weeks is generally not associated with additional gains.18 Meta-analyses study showed that PR significantly improves exercise capacity,18 depression and anxiety symptoms,19 and health-related quality of life18,20 in people with COPD. Despite evidence supporting the benefits of PR, poor adherence is common (noncompletion rate=10%–23%). Common barriers include environmental factors, as well as cognitive and behavioral factors such as a lack of perceived benefits of PR, current smoking habits, low motivation, poor physical ability, and psychological problems.21-23
Previous studies have demonstrated that symptoms of anxiety and depression are associated with poor disease prognosis in people with COPD. For instance, a meta-analysis by Atlantis et al6 reported that depression or anxiety symptoms consistently increased the risks of adverse COPD outcomes (relative risk=1.43; 95% CI: 1.22–1.68). Another meta-analysis24 found that comorbid anxiety more than doubled the risk of acute exacerbations within the first year after discharge (hazard ratio [HR]=2.10, 95% CI: 1.28–3.45), while comorbid depression elevated this risk by 36% (HR=1.36, 95% CI: 1.10–1.69).
In addition, Popa-Velea et al summarized key psychological variables that influenced COPD management and highlighted the importance of incorporating interventions addressing the psychological needs of the patients.25 Therefore, a growing body of evidence has examined the efficacy of psychological interventions defined as purposive and systematic approaches designed to reduce symptoms or modify behavior.26,27 Interventions such as cognitive behavioral therapy (CBT) aim to identify and change dysfunctional thinking and maladaptive behavioral patterns.7 Conversely, mindfulness-based interventions employ an acceptance-based approach to help individuals manage unhelpful thoughts or physical sensations, such as dyspnea.28 Ultimately, both approaches aim to address the individual's psychological problems.29 CBT has been shown to improve anxiety- and depression-related symptoms and enhance quality of life when compared with usual care.27 However, its efficacy in improving physical outcomes remains inconclusive.7,30 Conversely, mindfulness-based programs, such as relaxation and meditation31 have been shown to improve physical outcomes,30 although their effectiveness in improving psychological outcomes also remains inconclusive.30-32
Previous systematic reviews compared the efficacy of psychological intervention25 employing diverse approaches,17 e.g., CBT or mindfulness-based cognitive therapy, counseling, and psychoeducation. Among these, the majority of evidence reported their beneficial effects on psychological well-being.7,15,30 Exercise training, combined with psychological intervention, demonstrated profound clinical benefits, significantly improving quality of life and reducing emotional distress when compared with usual care alone.26 Although integrating psychological intervention with PR may enhance adherence and treatment efficacy in people with COPD, the synergistic effect is difficult to isolate, making it challenging to determine the exact added value of the psychological component. Standard PR traditionally includes education sessions focusing on understanding the disease and self-management; however, such education often lacks the targeted strategies to overcome the psychological barriers which disrupt the complex dyspnea-anxiety cycle. While standard PR effectively improves functional capacity, its independent impact on psychological symptoms remains inconsistent.26,27
Therefore, the current meta-analytical review aims to address this knowledge gap through synthesizing data from randomized controlled trials that directly compare PR combined with psychological intervention against conventional PR in order to establish whether structured behavioral strategies confer incremental benefits beyond standard care.
Methods
This review was performed in accordance with Preferred Reporting Items for Systematic reviews and Meta-Analyses (PRISMA) guidelines.33 The protocol for this study was registered in the International Prospective Register of Systematic Reviews (PROSPERO) under ID: CRD420250651201.
Search Strategy
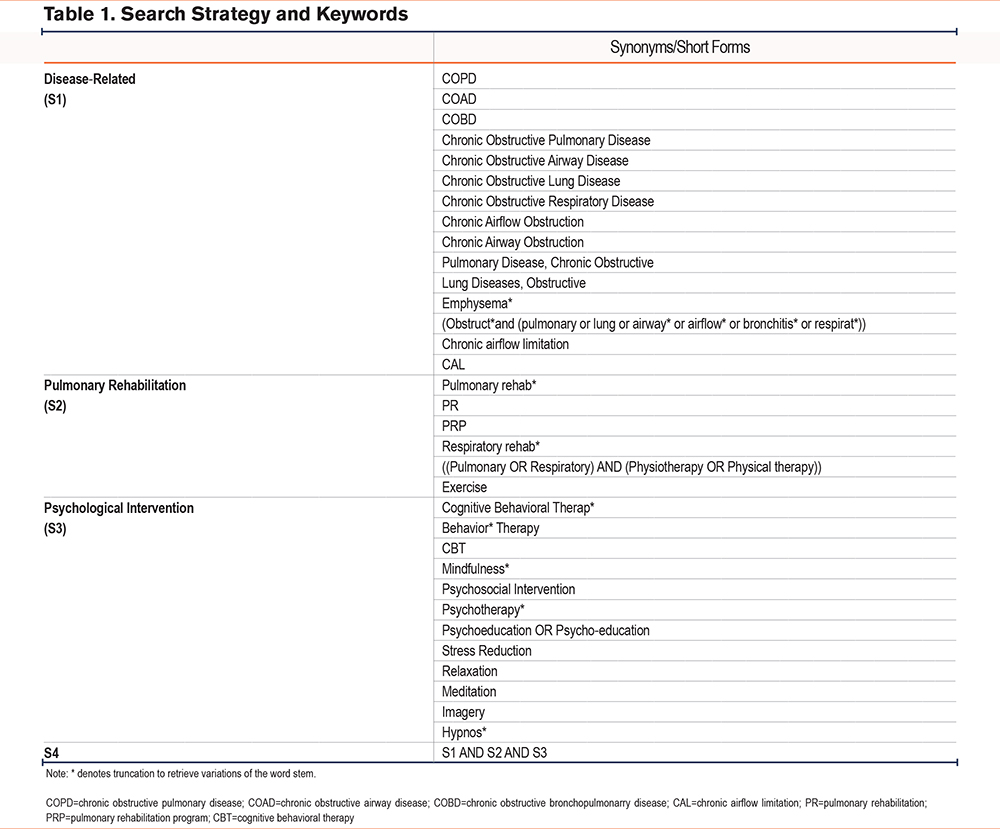
Four databases (i.e., PubMed, Embase, Web of Science, and the Cumulative Index to Nursing and Allied Health Literature via EBSCOhost) were searched for relevant articles from inception to March 31, 2025. All records retrieved from the database searches were exported to Microsoft Excel. Duplicates were identified and removed in Excel. The detailed search strategy is listed in Table 1.
Study Selection
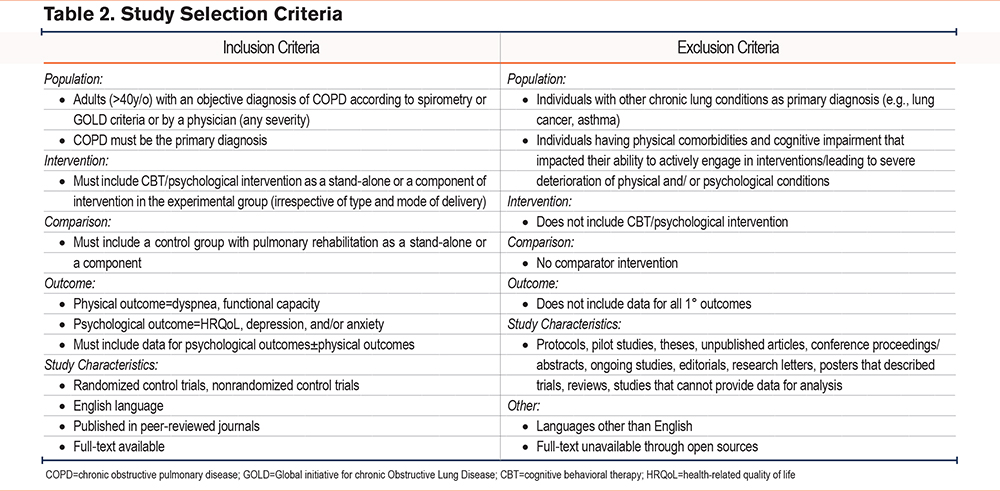
A detailed list of inclusion and exclusion criteria is provided in Table 2. Inclusion criteria included: (1) population: adults with COPD, (2) intervention: PR with an adjunctive CBT / psychological intervention (PSY-INT), (3) comparison: PR alone, (4) outcomes: all physical and/or psychological outcomes were considered, (5) study design: true experimental and quasi-experimental studies, (6) language: English, and (7) information source: full-text articles published in peer-reviewed journals. Studies were excluded if they did not fulfil the aforementioned inclusion criteria. Two authors (CC and TS) screened all studies independently, and discrepancies were resolved through discussion with a third author (GL).
Data Extraction
For each included article, article title, study year, and country of publication, demographics of participants, study methodology, intervention details, outcome measures, and results, including scores in specific outcome measures assessed before and after intervention treatment and/or between-group difference, were extracted independently by 2 authors (CC and TS). When studies reported multiple instruments for the same outcome domain, the decision of prioritization was based on predetermined clinical and methodological consideration.34,35
Quality Assessment
Each study was appraised independently by 2 authors (TSL and GLN). Disagreement on the scores was resolved by discussion, and a third author (CCC) was consulted when no consensus could be reached. Risk of bias was evaluated using the Cochrane Risk of Bias (RoB) 2 tool for randomized controlled trials,36 and ratings of “low risk”, “some concerns” or “high risk” were assigned to each domain. Certainty of evidence was evaluated using the Grading of Recommendations, Assessment, Development, and Evaluations (GRADE) approach37 and ratings of “high,” “moderate," “low,” and “very low” were assigned for each outcome. In addition to the quality assessment outlined in the protocol registered at PROSPERO (CRD420250651201), this review incorporated the Physiotherapy Evidence Database (PEDro) scale to evaluate the methodological quality of studies, complementing the Cochrane Risk of Bias tool to provide a comprehensive appraisal of study quality. A cut-off score of ≥6 on the PEDro scale indicated good methodological quality and a lower risk of bias.38
Statistical Analysis
Statistical and subsequent meta-analyses were performed using RevMan Manager 5.4 software. Quantitative data were expressed in mean ± standard deviation. Effect sizes were reported as standardized mean differences (SMD) with 95% CI. All meta‑analyses were conducted using a random‑effects model. Between‑study heterogeneity was quantified using the τ2 (Tau‑squared) statistic and the I2 statistic. In addition to the pooled effect and its CI, 95% prediction intervals (PIs) were calculated to estimate the range of true effects that may be expected in future populations. Sensitivity analyses were performed by excluding the study contributing most to statistical heterogeneity and re-estimating the pooled effect to assess the robustness of the findings.
Results
Screening
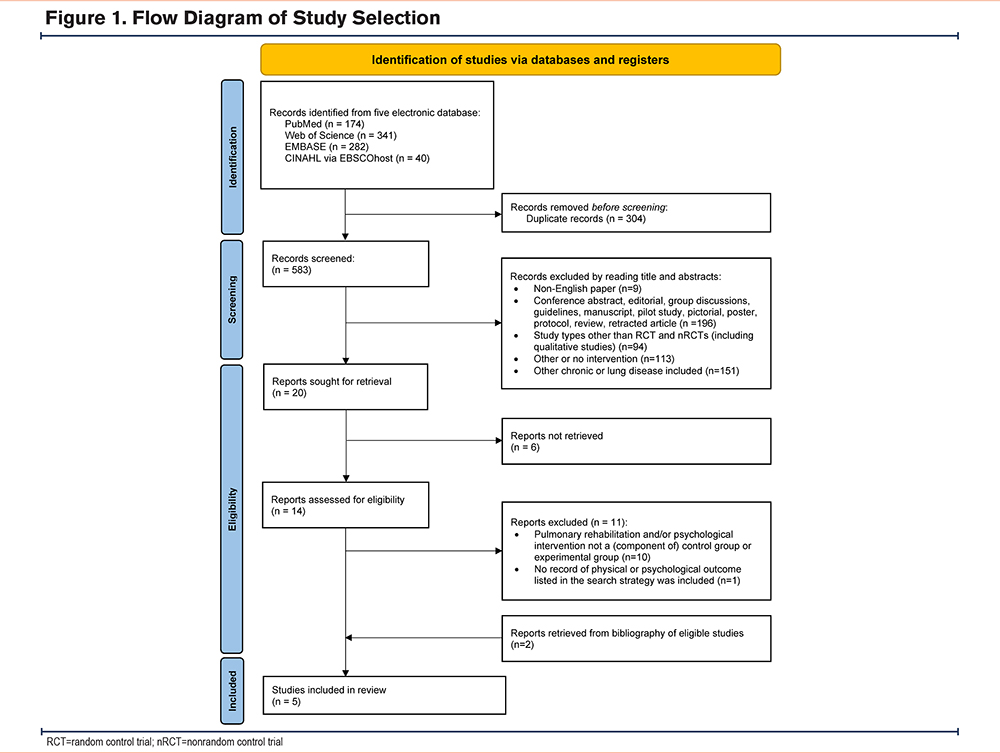
Study selection is illustrated in the PRISMA flow diagram (Figure 1). A total of 887 articles were retrieved from all databases. After removing 304 duplicates, an additional 469 articles were excluded during title and abstract screening. The remaining 20 were considered relevant for full-text review. Two articles were retrieved from the reference lists of included articles. After full-text screening, 5 articles met the inclusion criteria and were subjected to quality appraisal.39-43
Study Characteristics
A total of 276 participants (intervention group, n=138; control group, n=138) were included. Individuals were over 50 years of age. Studies were conducted in Australia (20%),42 Denmark (20%),40 Canada (20%),43 and Brazil (40%).39,41 COPD severity ranged from moderate to severe. Three studies employed GOLD criteria to classify disease stage,40,41,43while the remainder used either the Brazilian Society of Pulmonary and Tisiology guidelines39,41or forced expiratory volume in 1 second to forced vital capacity ratio33 (Table 3). One study did not specify the tool used for classification.42
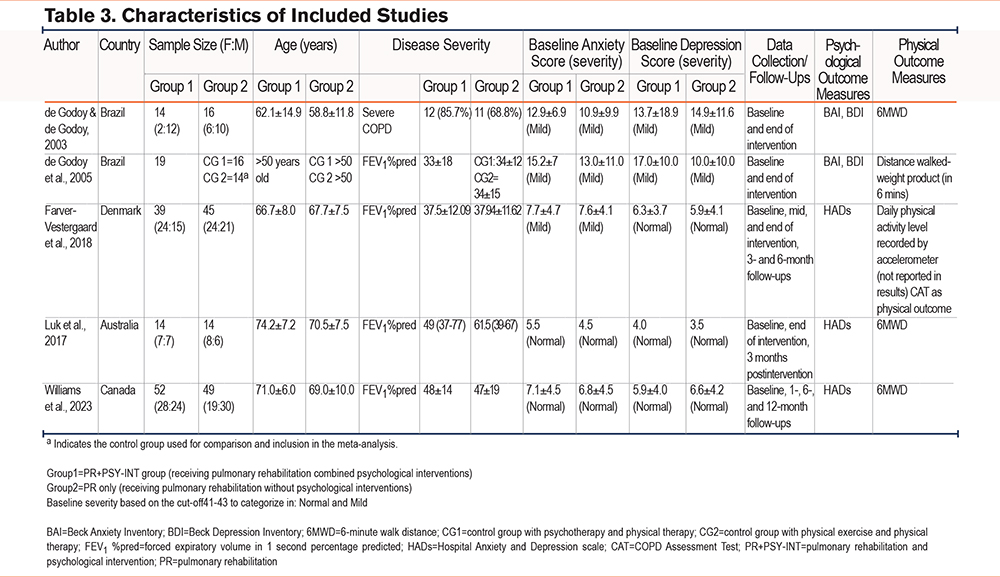
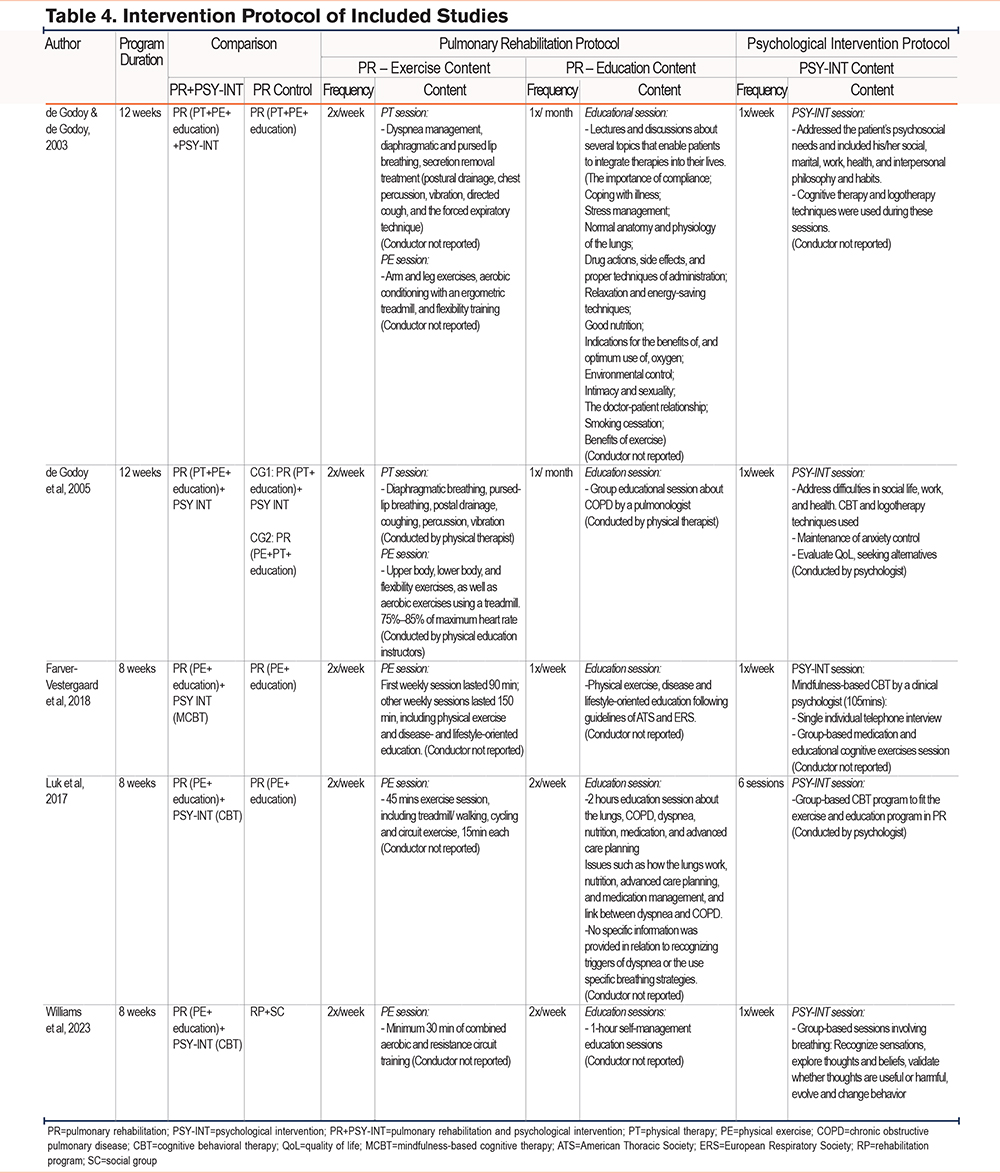
All studies compared PR+PSY-INT with active control groups consisting of PR, education, and a social group (Table 4).39-43 The contents of the psychological interventions varied. Most studies included individual or group-based CBT.39-42 Other approaches (e.g., psychotherapy) were also used.41 Three studies offered 8-week interventions,40,42,43 while 2 studies provided 12-week interventions.39,41 To evaluate the add-on benefits of psychological interventions on anxiety and depression symptoms, studies utilized the Hospital Anxiety and Depression Scale (HADS),40,42,43 Beck Anxiety Inventory (BAI), and Beck Depression Inventory (BDI)39,41 as outcome measures. For physical outcomes, 3 studies used the 6-minute walk distance (6MWD),39,42,43 while one study used the distance walked-weight product (in 6 minutes).41
Quality Appraisal
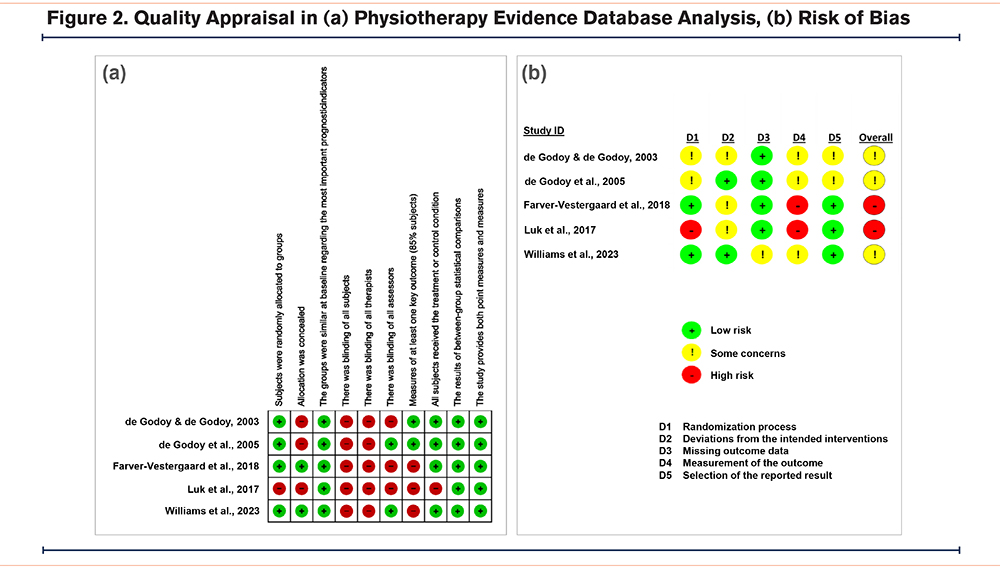
PEDro results are summarized in Figure 2a. Four studies39-41,43 scored 6 or above on the PEDro scale, while one study42 had a score of 3. All 5 studies had similar baseline characteristics between treatment and control groups and reported at least one key outcome for between-group comparisons. RoB 2 results are summarized in Figure 2b, 2 studies were considered to have a high risk of bias. These 2 studies were raised regarding the dominant 4 measurement outcome,40,42 and one study had a high risk of the randomization process.42
Certainty of Evidence
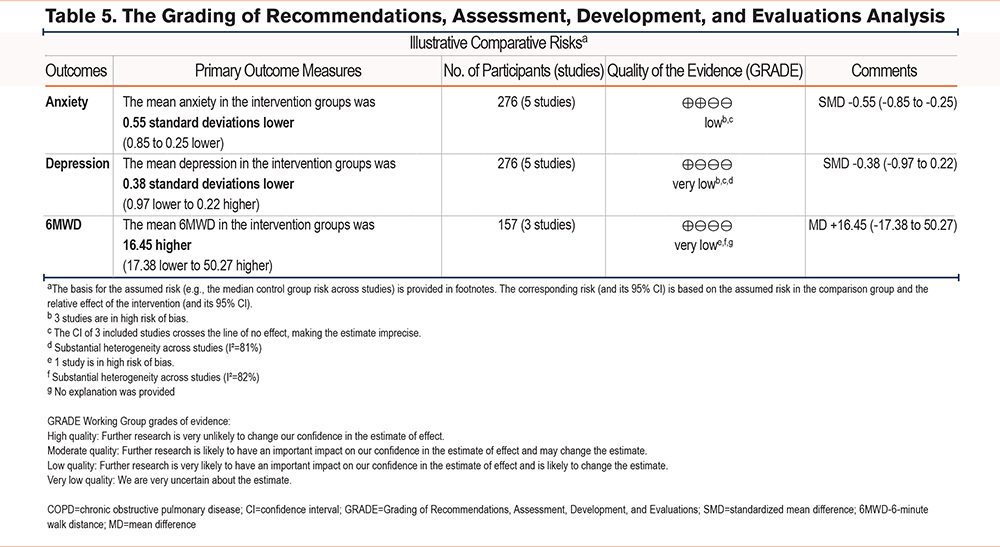
GRADE results are reported in Table 5. Changes in the levels of anxiety, depression, and 6MWD were rated as very low certainty of evidence.
Effects of Combined Therapy (Pulmonary Rehabilitation+Psychological-Intervention) on Psychological Outcomes
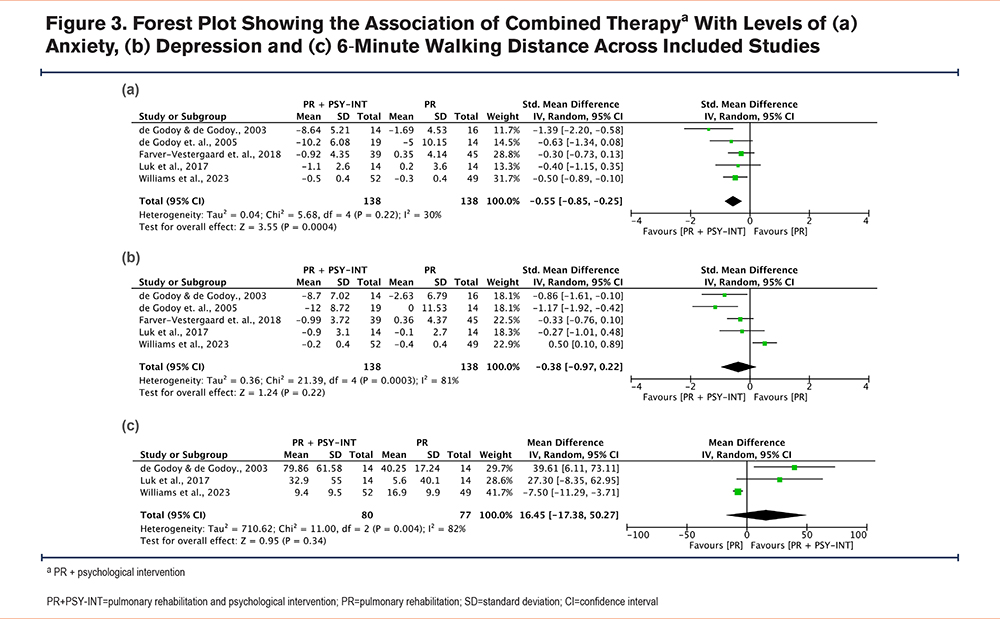
Five studies investigated the effects of PR+PSY-INT on anxiety symptoms compared to PR alone (Figure 3a). Three studies adopted the HADs-anxiety subscale (HADS-A),40,42,43 and 2 used the BAI.39,41 The random‑effects model showed heterogeneity I2 was 30%. The pooled effect demonstrated a statistically significant reduction in anxiety symptoms in the PR+PSY-INT group (SMD =-0.55; 95% CI: -0.85 to -0.25; p<0.001). With the 95% PI (-1.35 to 0.25), the effect favors PR+PSY-INT, but the true effects across different settings and populations may range from a substantial reduction in anxiety symptoms to little or no improvement.
The overall effect of PR+PSY-INT on depression symptoms was not statistically significant (SMD=-0.38, 95% CI=-0.97 to 0.22, p=0.22). The 95% PI was wide (-2.52 to 1.76). Four out of 5 studies measured SMD favoring PR+PSY-INT on depression symptoms (Figure 3b).39-42 The heterogeneity of the overall pooled data was 81%. Three studies used the HADs-depression subscale (HADS-D)40,42,43 and 2 used the BDI39,41 to assess depression symptoms.
Effects of Combined Therapy (Pulmonary Rehabilitation+Psychological-Intervention) on Physical Outcomes
Three studies compared the effects of PR+PSY-INT versus control conditions on 6MWD.39,42,43 PR+PSY-INT did not significantly improve 6MWD compared with the control conditions (MD=16.45 m, 95% CI −17.38 to 50.27; p=0.34), with substantial heterogeneity observed (I2=82%; Figure 3c).
Sensitivity Analysis
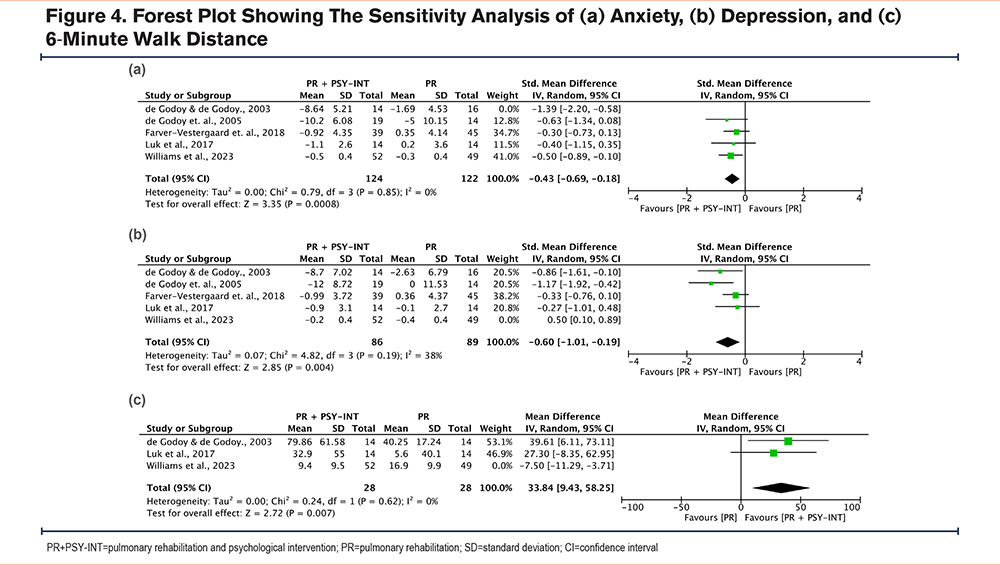
Sensitivity analyses were conducted to assess the robustness and consistency of the overall findings. For anxiety symptoms, heterogeneity (I2) decreased from 30% to 0% after excluding the study by de Godoy et al,39 while the adjusted pooled estimate remained statistically significant (SMD=-0.43, 95% CI=-0.69 to -0.18, 95% PI=-0.98 to 0.12, p < 0.001, 95%, Figure 4a). This indicates that this study was the main contributor to heterogeneity regardless of the outcome measure used. For depression symptoms, heterogeneity was initially high. A study of Williams et al43 reported an effect in the opposite direction, and its exclusion reduced I2 from 81% to 38% and changed the pooled effect from nonsignificant to statistically significant (SMD=-0.60, 95% CI=-1.01 to -0.19, 95% PI=-2.05 to 0.85, p=0.004, Figure 4b). A similar pattern was observed for the 6MWD. Removing the study of Williams and colleagues,43 the I2 reduced from 82% to 0% and yielded a significant improvement (MD=33.84, 95% CI=9.43 to 58.25, p=0.007, Figure 4c), suggesting that this study’s results were inconsistent with the others. One plausible explanation is the variation in assessment timepoints, most studies measured outcomes immediately postintervention,39-42 whereas Williams et al assessed outcomes 1-month after intervention.43 Given uncertainty about how long the intervention effect lasts, differences in follow‑up timing may be one issue contributing to the observed heterogeneity.
Subgroup Analysis on the Factors Affecting the Effects of Pulmonary Rehabilitation+Psychological-Intervention
Baseline Level of Anxiety/Depression Symptoms
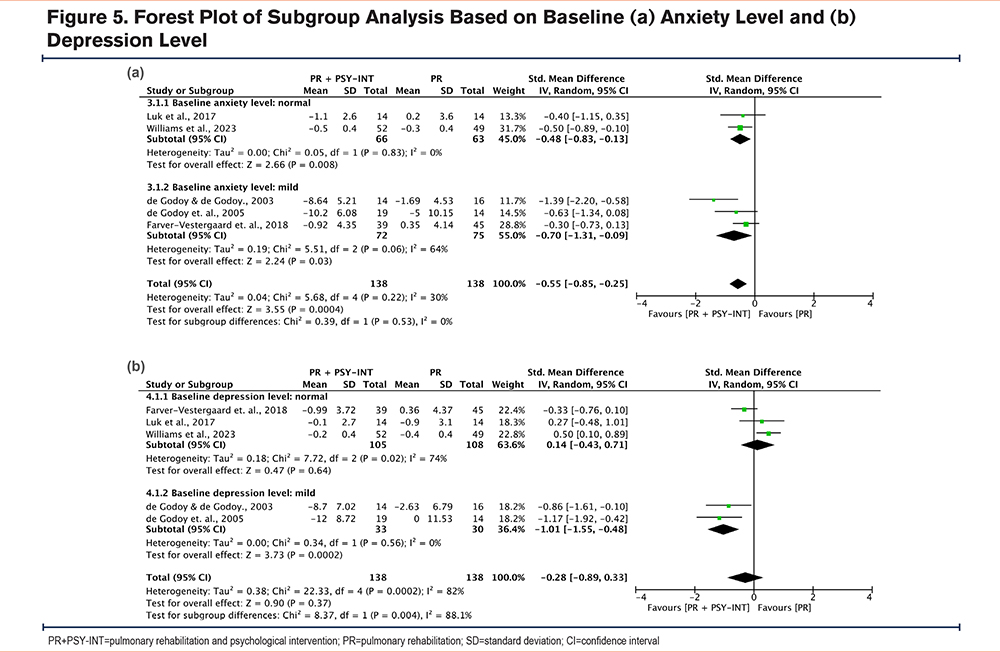
People with mild and normal anxiety symptom levels at baseline demonstrated significant improvement (normal: SMD=-0.48, 95% CI=-0.83 to -0.13, p=0.008; mild: SMD=-0.70, 95% CI=-1.31 to -0.09, p=0.03) (Figure 5a). There are no significant differences between the subgroups (p=0.53). For depression symptoms, only patients with mild symptoms at baseline showed significant improvement (SMD=-1.01, 95% CI=-1.55 to -0.48, p=0.0002). Significant differences were observed between the subgroups (p=0.004, Figure 5b).
Intervention Dosage
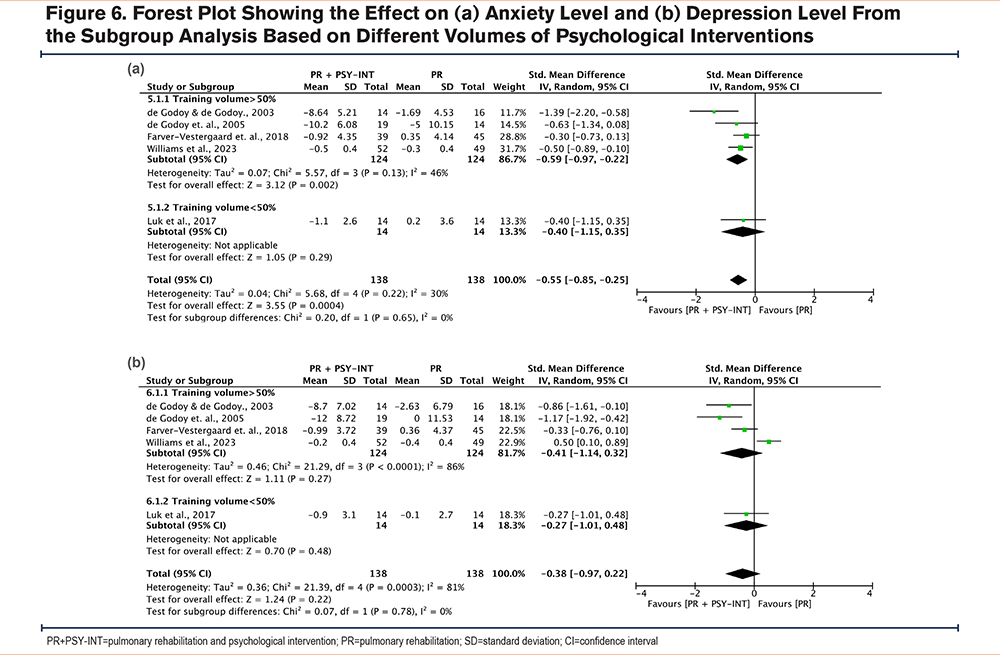
A significant effect that favors PR+PSY-INT was only observed in the subgroup with high volumes of CBT (≥ 50% of total sessions)39,41,42 for outcomes in anxiety symptoms (SMD=-0.59, 95% CI=-0.97 to -0.22, p=0.002), although the subgroup difference was insignificant (Figure 6a). Depression showed no subgroup difference and effect (Figure 6b).
Discussion
In line with the review by Popa-Velea et al,25 this meta-analysis contributes new insights by pooling effect estimates of outcome measures and critically appraising study quality to justify the strength of the evidence.37 Furthermore, this meta-analytical review highlights the added value of PSY-INT on both psychological and physical outcomes in people with COPD undergoing PR. By comparing the combined intervention of PSY-INT plus PR against PR alone, the incremental effects of PSY-INT can be clarified. The pooled data from included studies demonstrated significant benefits for anxiety symptoms when PSY-INT was incorporated into PR for people with COPD.
Additive Effects of Psychological Intervention on Psychological Outcomes
This review evaluated the comparative efficacy of PR+PSY-INT and PR alone for improving psychological and physiological outcomes in people with COPD. Overall, PR+PSY-INT demonstrated superior effects on anxiety symptoms compared with PR alone, whereas no clear additional benefit was observed for depression symptoms. For physiological outcomes, PR+PSY-INT did not consistently outperform PR alone, and effects varied across measures and studies. We have also performed additional analyses comparing the MD of each outcome measurement with their minimal (clinically) important differences (MCID/MID). For anxiety symptoms, both BAI and HADS-A results showed significant mean differences favoring PSY+PR, but only one study by de Godoy et al could meet the respective MCID or MID44,45 (BAI: MID=8.8; HADS-A: MCID=1.6). This showed that notwithstanding the overall improvements of anxiety symptoms favoring PR+PSY-INT, the clinical importance of such effects was doubtful. In addition, the 95% PI for anxiety symptoms (-1.35 to 0.25) indicates the average effect is a beneficial true effect and in future settings may range from a reduction to little or no improvement. The substantial study effect observed for anxiety and depressive symptoms in the present review aligns with recent high-power clinical evidence as reported by Taylor et al.46 The study evaluated the effect of psychological interventions on people with COPD and found that there was no significant overall effect on depression. Brief psychological approaches often face severe real-world barriers, including deeply entrenched, lifelong comorbidities, complex social situations, and poor subsequent uptake of physical rehabilitation. The psychological approach was largely ineffective because it was delivered late in the trajectory of advanced, disabling COPD, acting as “too little, too late” for entrenched distress. Crucially, the study hypothesized that the efficacy of such behavioral modalities may be contingent upon early-stage deployment. Also, the psychological interventions were profound therapeutic resistance when distress had become clinically entrenched alongside lifelong multicomponent conditions, such as health conditions, complex social backgrounds, and severely attenuated behavioral engagement. The variations in baseline clinical severity and the precise timing of intervention deployment across primary studies naturally explain the wide PIs, which represent the difference between study variability.
Apart from the overall effect, one study47 compared the discriminant validity of HADS and BDI-II/BAI in detecting depression in people with COPD and suggested that after the removal of “question 4: I feel as if I am slowed down” and adjusting the cut-off point to ≥5, the HADS-D sensitivity/specificity would improve from 78%/81% to 100%/83%. It was suggested that the feeling of “slowed down” could be universal in people with COPD, hence, lowering the sensitivity of the scale to detect changes in depressive symptoms.47 A similar problem was identified in BDI-II in “question 21: loss of interest in sex.”47 Additionally, a subgroup analysis44 showed that only those studies employing BDI as an outcome measure for depression symptoms showed a statistically and clinically significant added effect favoring the PR+PSY-INT (BDI: MD=-8.44) but not in HADS-D (Chi2=6.13, p=0.01, I2=83.7%). Considering the above-discussed questionable sensitivity in detecting the changes of depressive symptoms in people with COPD, plus the relatively high heterogeneity and lack of significant overall effects of the PR+PSY-INT on outcomes of depression symptoms in this study, the corresponding summarized result warrants cautious interpretation. Consistently, the 95% PI for the outcome of depression symptoms was very wide (-2.52 to 1.76), implying substantial between-study heterogeneity. These results implied the necessity to adjust assessment items in future studies to augment the specificity of outcome measurement for this disease population.
Nonetheless, disease-specific fears also play an important role in the subjective experience of people with COPD that exceeds the effects of general, unspecific forms of anxiety.48 It is mentioned that generic measurements such as HADS and BDI are fundamentally insufficient to capture the specific emotional burdens of specific disease populations. Consequently, the widespread reliance on these generic scales across the studies may present a profound psychometric limitation that attenuates evaluative sensitivity, which naturally explains the lack of statistically significant overall treatment effects and the substantial study heterogeneity observed in our review. In short, future research with more robust designs and consistent outcome measures is required to confirm and provide evidence of the effects of PR+PSY-INT on depression in people with COPD.
Additive Effects of Psychological Intervention on Physical Outcomes
In terms of physical outcomes, PR is well established for improving the 6MWD. As PR alone already substantially improves physical capacity, there are limited additional gains when adding PSY-INT. While the addition of PSY-INT may offer some extra benefit, the net change in 6MWD did not reach statistical significance compared to PR alone. Nonetheless, the sensitivity analysis for the 6MWT showed a wide 95% PI (–99.35 to 154.25m). This suggests considerable clinical and methodological heterogeneity, meaning that while some subgroups may experience meaningful gains, others may not. Previous systematic reviews reported that PSY-INT could significantly improve exercise capacity and dyspnea in people with COPD compared to passive or active control.15,26,30 This improvement might be a result of the interrelationship of physical and psychological factors in COPD.15 For instance, people with dyspnea might undergo cognitive and emotional processes, which potentially lead to the development of anxiety and/or depression symptoms.15 Having these psychological issues prompts the avoidance of physical activities, leading to deterioration in physical capacity.24,26 However, the data on changes in dyspnea level from the included studies are insufficient to substantiate the correlation between physical and psychological outcomes. Hence, we could not conclude if such an effect is due to the dyspnea-inactivity-deconditioning cycle as discussed in the introduction. Meanwhile, the wide PI is consistent with this rationale, as the functional response may vary if psychological burden, dyspnea severity, or program intensity differs across studies. Nevertheless, it was observed that the 3 studies that had the largest effect on anxiety symptoms, favoring PR+PSY-INT,39,41,42 also demonstrated a greater improvement on physical outcomes, favoring the experimental group. This indicates a possible link between anxiety symptoms and physical outcomes. Future research should standardize 6MWT procedures and report intervention fidelity to reduce dispersion in effects and clarify which subgroups derive clinically meaningful improvements. Future research could investigate the proposed correlation by measuring the change in dyspnea level alongside physical and psychological outcomes.
Factors That Influence the Outcome Measures
With reference to the defined cut-offs,49,50 the mean severity of anxiety and depression symptoms of the participants in the included studies ranged from minimal to mild. The subgroup analysis revealed that patients with clinically observed anxiety and depressive symptoms at baseline demonstrated significant changes in psychological outcomes, although the between-group difference in anxiety was insignificant. Acknowledging the higher responsiveness by participants with baseline psychological symptoms, PR+PSY-INT might not be recommended for all patients, rather only limited to the abovementioned subgroup for resource concerns. Nonetheless, no study included participants with severity of anxiety/depression symptoms graded as moderate or severe, hence the added effects of PSY-INT on these patient populations are unclear. Future studies could, therefore, analyze the added benefits of PSY-INT on improving psychological outcomes for individuals with different severities of anxiety/depression symptoms accordingly.
According to the dosage of programs, weekly sessions demonstrated a significantly larger effect on anxiety symptoms. In contrast, programs by Luk et al42 where only 3 or 6 sessions were delivered in 8 weeks, respectively, showed insignificant improvements on psychological outcomes. This suggested that weekly PSY-INT may be more favorable to facilitate improvement in health outcomes. However, the insignificant subgroup difference indicated that weekly sessions may not impose significantly different effects on psychological outcomes compared to less frequent sessions. For the duration of each session, only Farver-Vestergaard et al stated the length of PSY-INT as 45 minutes40; no statistical analysis could, therefore, be conducted. These uncertain and inconsistent findings warrant more studies to examine the relationship between program duration and the effectiveness of the intervention.
Study Limitations
There are several limitations in this review. First, the limited number of studies included reduces statistical power, which affects subsequent interpretation and recommendations. Secondly, the low quality of studies and the certainty of outcome measurements based on the GRADE analysis limited our confidence when generating clinical recommendations. Thirdly, insufficient data were acquired for each subgroup analysis, which restricted the confidence of our results. Hence, conclusions regarding the optimal treatment duration and long-term effects of PSY-INT on an existing PR program could not be made. Fourthly, the comparison design of this review does not allow for direct comparison with active control. This comparison limits the ability to rule out nonspecific therapeutic effects. As highlighted by Williams et al, the intervention shows significant benefits when compared to inactive controls, but these benefits disappear when compared to active controls.27 Consequently, the comparison design on this review may have led to an overestimation of the specific incremental effect size of PSY-INT. Fifth, blinding of patients and therapists is structurally impossible due to the active nature of the interventions.
One point to take note of was that one study reported multiple outcomes to assess the domain of depression.42 In that study, both HADS and Depression Anxiety Stress Scale (DASS) demonstrated trends of favoring PSY-INT+PR more than PR only. However, only DASS demonstrated a statistically significant difference. Such a phenomenon could probably be associated with the differences in tool sensitivity. Although both scales are comparable instruments for evaluating depression, their item content differs, which can result in varying sensitivities.51 Despite these variations, in this meta-analytical review, only HADS-D was extracted for data synthesis due to the predetermined prioritization of outcomes, which potentially reduced any potential selection bias. Consequently, this approach may result in an underestimation of the intervention effect on the pooled data.
Conclusions
Combining psychological intervention with PR for COPD has become an increasingly popular research topic in recent years owing to its proposed effect on breaking the dyspnea-inactivity-deconditioning vicious cycle. Our study revealed that PSY-INT complementary to PR provides additional benefits on anxiety symptoms in people with COPD (SMD=-0.55, 95% CI: -0.85, -0.25, P=0.0004), although no statistically significant improvement was observed for depression (SMD=-0.38, 95% CI: -0.97, 0.22, P=0.22). However, greater treatment effects were found in patients with clinically observed psychological symptoms at baseline. Regarding the intervention dosage, a higher volume PSY-INT possibly induces greater improvement in anxiety and depression symptoms based on the limited data provided by the included studies. Further research could supplement the mechanism through which PSY-INT induces an additive effect in psychological and physical outcomes when added to PR and investigate the possible correlation between PSY-INT volume and baseline psychological symptoms severity with treatment effectiveness.
Acknowledgements
Author contributions: CCC, GLN, and TSL were responsible for study screening, data extraction, and the initial drafting of the manuscript. FFW, TKF, and TM contributed to data analysis and interpretation, visualization, and manuscript revision and editing. XCF, BY, JNC, and BWL contributed to data validation and the critical review of the manuscript. SPN served as the senior author and provided overall study conceptualization, supervision, and oversight of the entire review process, including systematic manuscript writing and revision. All authors approved the final version of the manuscript submitted for publication.
Declaration of Interest
The authors confirm they have no conflicts of interest.